

Dr. Suzanne McMurry, N.D., F.A.B.N.O.
Integrative oncologist and naturopathic physician who completed an accredited hospital-based integrative oncology residency. She is a Fellow of the American Board of Naturopathic Oncology and provides evidence-based support before, during, and after cancer treatment.
Last reviewed: August 31, 2026
Every so often a study comes along that changes what we’re allowed to say in clinic. For years, those of us in integrative oncology have told patients that exercise after treatment was associated with better outcomes, always with the careful caveat: “but that’s observational data; we can’t prove the exercise is doing it.”
The CHALLENGE trial strengthened that evidence for a specific group: people with resected colon cancer who had completed adjuvant chemotherapy.
In plain terms, CHALLENGE was a large randomized trial showing that participants assigned to a supervised, progressive exercise program sustained for three years had better disease-free survival than those who received health-education materials alone. Exercise was added after standard treatment; it did not replace surgery, chemotherapy, surveillance, or oncology care.
Most coverage of the trial has been either breathless (“exercise beats chemo!” — no) or buried in academic hedging. As a naturopathic oncologist, my job is the middle path: what the study actually found, what it does not prove, and how to discuss safe, individualized movement with your care team.
TL;DR: The CHALLENGE trial in four sentences
- The trial enrolled people with resected colon cancer who had completed adjuvant chemotherapy.
- The intervention was supervised, progressive, and sustained for three years, with coaching and individualized activity goals.
- Participants assigned to the exercise program had better disease-free survival than those who received health-education materials alone; this tested exercise after standard treatment, not instead of it.
- The practical takeaway is to discuss a safe, individualized, progressive exercise plan with your oncology and rehabilitation team—especially because results from this colon-cancer population should not be generalized automatically to every cancer or treatment phase.
About the download: the 12-week plan below is an educational on-ramp for a care-team conversation. It does not reproduce the three-year CHALLENGE intervention and is not a substitute for individualized oncology, rehabilitation, or exercise guidance.
What the CHALLENGE Trial Actually Did
The Colon Health and Life-Long Exercise Change trial (yes, someone worked hard on that acronym) followed colon cancer patients who had finished surgery and adjuvant chemotherapy, the group whose biggest remaining question is “will it come back?”
Researchers randomized roughly 890 patients to one of two groups:
- The exercise group received a supervised, progressive program: a personal physical activity consultant, an individualized exercise plan, and regular coaching sessions sustained over three years. The target was a sustained increase in weekly aerobic activity, the equivalent of adding about 3 to 4 brisk 45-to-60-minute walks per week.
- The comparison group received standard health education materials promoting exercise and healthy eating, which, notably, is more than many patients get.
Then they followed everyone for years. This design matters: it’s the difference between “people who exercise do better” (which could just mean healthier people exercise more) and “being assigned to exercise made people do better.” CHALLENGE is the second kind, a randomized phase 3 trial, the same standard of evidence we demand from drugs.
What It Found
Two headline results, published in the New England Journal of Medicine in 2025:
- Fewer recurrences. Disease-free survival at five years was about 80% in the exercise group versus about 74% in the comparison group, roughly a 28% reduction in the risk of recurrence, new cancer, or death.
- Longer lives. Overall survival at eight years was about 90% in the exercise group versus about 83%, roughly a 37% reduction in the risk of death.
Important context: these results came from adding supervised, progressive exercise after surgery and adjuvant chemotherapy. They do not show that exercise replaces standard cancer treatment.
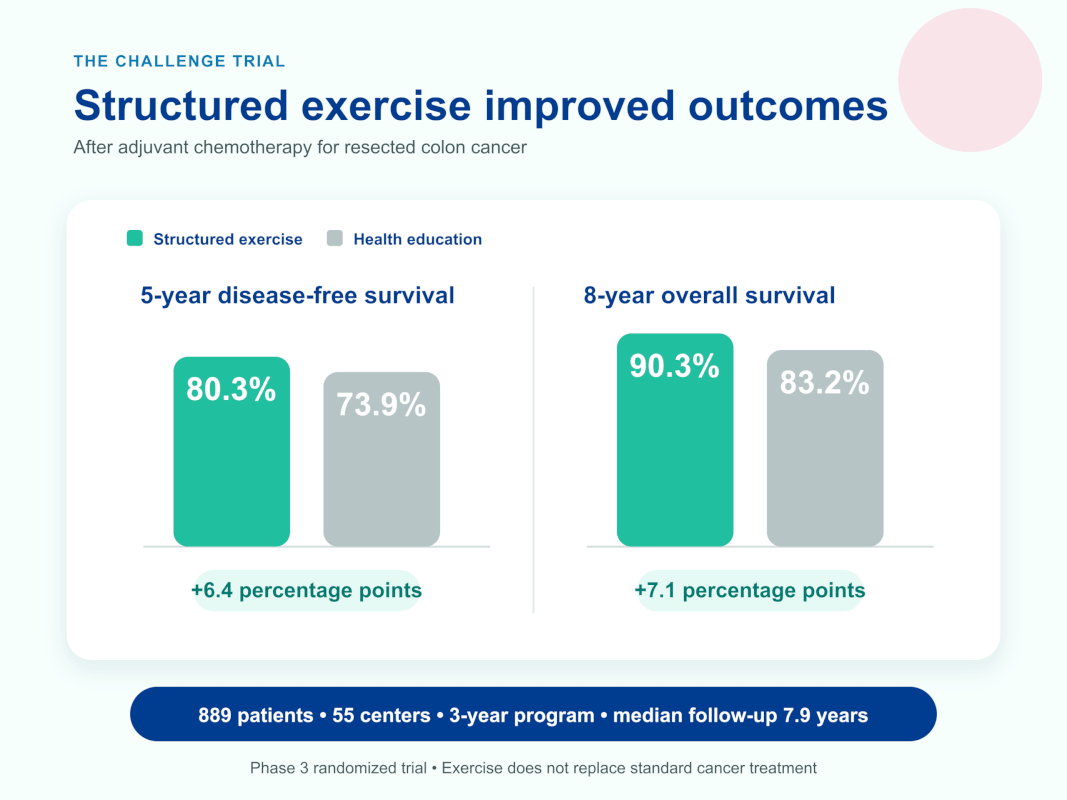
The absolute differences are clinically meaningful, but this was not a head-to-head comparison with chemotherapy. The exercise program was studied after surgery and adjuvant chemotherapy, alongside standard surveillance and oncology care.
That’s the part worth sitting with. Not exercise instead of chemotherapy; these patients had already completed chemo. Exercise after treatment, as its own additional layer of protection.
What This Study Does NOT Tell Us
This is the section the breathless headlines skip, so let’s be precise:
- It’s a colon cancer trial. The randomized proof applies to colon cancer survivors after adjuvant chemo. For breast, prostate, lung, and other cancers we have large, consistent observational data linking activity to lower recurrence and mortality, plus randomized trials showing exercise improves fatigue, cognition, treatment tolerance, and quality of life. Strong supporting evidence, but CHALLENGE-level proof exists today only for colon cancer.
- It does not replace standard treatment. Participants completed surgery and adjuvant chemotherapy first. Anyone using this trial to argue for skipping conventional treatment is misreading it badly, and that misreading is dangerous.
- It tested a program, not just movement. Participants received supervision, coaching, accountability, and a progressive plan sustained for three years. The lesson isn’t “buy a treadmill”; it’s that structure and support are part of the medicine.
- It’s a starting dose, not a ceiling or a floor. The trial’s target was moderate. What we know works is the consistent, modest, sustained dose.
The Prescription, Translated
The CHALLENGE intervention was supervised, progressive, individualized, and sustained for three years. The simplified framework below is a conversation starter, not a reproduction of the trial protocol and not a prescription for everyone:
- Aim for the equivalent of 3 to 4 brisk 45-to-60-minute walks per week. “Brisk” means you’re slightly breathless but can still hold a conversation.
- Walking is the proven default, but the currency is effort, not steps. Cycling, swimming, dancing, hiking, rowing: anything aerobic at conversational-but-breathy intensity counts.
- Add 2 short strength sessions per week (bands, bodyweight, light weights). This wasn’t CHALLENGE’s focus, but it’s standard exercise oncology guidance and protects the muscle and bone your recovery depends on.
Modifications that make it work in the real world:
- Starting from deconditioned: begin at 10 to 15 minutes at whatever pace you have, and add 5 minutes per week.
- Neuropathy in the feet: stable surfaces, supportive shoes, and consider a stationary bike or pool walking.
- Joint pain on aromatase inhibitors: warm up longer and favor low-impact options.
- Bone metastases or significant bone thinning: ask for an oncology-trained physical therapist referral before starting.
Your 12-Week Restart Plan
This 12-week educational plan is a gradual conversation starter. It does not reproduce the supervised, progressive three-year CHALLENGE intervention and is not a substitute for individualized oncology, rehabilitation, or exercise guidance.
Before starting, review the plan with your care team—especially if you are in treatment, recently had surgery, have a heart or lung condition, bone metastases, neuropathy, balance concerns, severe fatigue, or other mobility or safety limitations.
Weeks 1-2: Re-introduce. Walk 10 to 15 minutes, 3 days this week, at an easy pace. The goal is showing up, not speed.
Weeks 3-4: Stabilize. Walk 20 minutes, 3 to 4 days per week. Add one 10-minute strength session: sit-to-stands from a chair, wall push-ups, and a light band row.
Weeks 5-6: Build. Walk 25 to 30 minutes, 4 days per week, and on two of them push the middle 10 minutes to “slightly breathless.” Strength moves to 2 short sessions per week.
Weeks 7-8: Consolidate. 30 to 35 minute walks, 4 days per week, brisk for at least half. Keep both strength sessions.
Weeks 9-10: Approach the dose. Three to four walks of 40 to 45 minutes, mostly brisk.
Weeks 11-12: Arrive. You’re at or near the CHALLENGE target: 3 to 4 brisk 45-minute sessions plus 2 strength sessions per week.
Across all twelve weeks, increase only as tolerated and pause for new or worsening symptoms. On low-energy days, the safest choice may be a gentler version, rest, or contacting your care team.

You Weren’t Meant to Do This Alone (Neither Were the Trial Participants)
Remember: CHALLENGE participants followed a supervised, progressive program with a physical activity consultant and three years of sustained coaching. Structure and accountability were part of the intervention. Your version of that support might be:
- An oncology-trained exercise professional. Look for the ACSM/ACS Certified Cancer Exercise Trainer credential, or ask your cancer center about exercise oncology programs.
- An oncology-trained physical therapist, especially if neuropathy, bone concerns, surgery recovery, or deconditioning make starting feel risky.
- A standing date. A neighbor, walking group, or survivor program can make consistency easier.
- An integrative care plan that makes exercise possible. Fatigue, joint pain, neuropathy, poor sleep, and low iron are treatable barriers.
Why People Stall, and What Helps
- “I’m too exhausted.” Start with five minutes. Read my complete guide to cancer-related fatigue, and have profound exhaustion evaluated.
- “It hurts.” Low-impact options and longer warm-ups can bend the plan without canceling it. New, focal, or worsening pain needs a call to your team first.
- “I’m afraid I’ll hurt myself.” A supervised start with a PT or cancer exercise trainer converts fear into confidence.
- “I don’t have time.” The dose is about three hours per week. Two 20-minute walks count more than one 45-minute walk that never happens.
Frequently Asked Questions About the CHALLENGE Trial and Exercise
What did the CHALLENGE trial show?
CHALLENGE was a randomized phase 3 trial of about 890 people with resected colon cancer who had completed adjuvant chemotherapy. Those assigned to a supervised, progressive exercise program sustained for three years had higher disease-free survival and overall survival than those given health-education materials alone.
Can exercise really prevent cancer recurrence?
For this post-adjuvant colon-cancer population, CHALLENGE provides randomized evidence that assignment to a supervised, progressive exercise program improved disease-free survival. It does not guarantee that exercise prevents recurrence for an individual, and it should not be generalized automatically to other cancers.
How much exercise do cancer survivors need?
The trial used an individualized, supervised, progressive program sustained for three years, with an aerobic activity target roughly equivalent to 3 to 4 brisk 45-to-60-minute walks per week. Strength training is common in broader exercise-oncology guidance but was not the core CHALLENGE intervention. The right starting point depends on treatment status, symptoms, mobility, and safety.
Is it safe to exercise after cancer treatment?
For most survivors, yes. Specific situations such as bone metastases, severe neuropathy, heart conditions, or very low blood counts call for a tailored plan and supervision.
Does this mean exercise works better than chemotherapy?
No. Participants had already completed surgery and adjuvant chemotherapy. Exercise was added after standard treatment; it did not replace surgery, chemotherapy, surveillance, or oncology care.
I had a different cancer. Does CHALLENGE apply to me?
The randomized survival evidence is specific to people with resected colon cancer after adjuvant chemotherapy. Evidence supports exercise for outcomes such as fatigue, function, mood, and quality of life across many cancer populations, but the survival result should not be assumed to apply identically to every cancer or treatment phase.
The Most Encouraging Trial in Years
Cancer survivorship is full of things you can’t control. CHALLENGE gave a defined post-treatment colon-cancer population phase 3 evidence for a supervised, progressive non-drug strategy added after standard care, one that also happens to improve fatigue, brain fog, sleep, and mood.
If symptoms or uncertainty are standing between you and week one, that’s a solvable problem. Building a safe, personalized exercise foundation in coordination with your oncology and rehabilitation team is exactly the kind of work I do with survivors every week.
Schedule a virtual consult to build your post-treatment exercise plan, and recover better, faster:
References
- Courneya KS, Vardy JL, O’Callaghan CJ, et al.; CHALLENGE Investigators. Structured Exercise after Adjuvant Chemotherapy for Colon Cancer. N Engl J Med. 2025;393(1):13–25. doi:10.1056/NEJMoa2502760.
- Campbell KL, Winters-Stone KM, Wiskemann J, et al. Exercise Guidelines for Cancer Survivors: Consensus Statement from International Multidisciplinary Roundtable. Med Sci Sports Exerc. 2019;51(11):2375–2390. PMID: 31626055.
- Holmes MD, Chen WY, Feskanich D, Kroenke CH, Colditz GA. Physical activity and survival after breast cancer diagnosis. JAMA. 2005;293(20):2479–2486. PMID: 15914748.
- Kenfield SA, Stampfer MJ, Giovannucci E, Chan JM. Physical activity and survival after prostate cancer diagnosis in the Health Professionals Follow-Up Study. J Clin Oncol. 2011;29(6):726–732. PMID: 21205749.
- ClinicalTrials.gov. NCT00819208: Colon Health and Life-Long Exercise Change (CHALLENGE).
- American College of Sports Medicine. Exercise and Cancer resources.
